
What Is It?
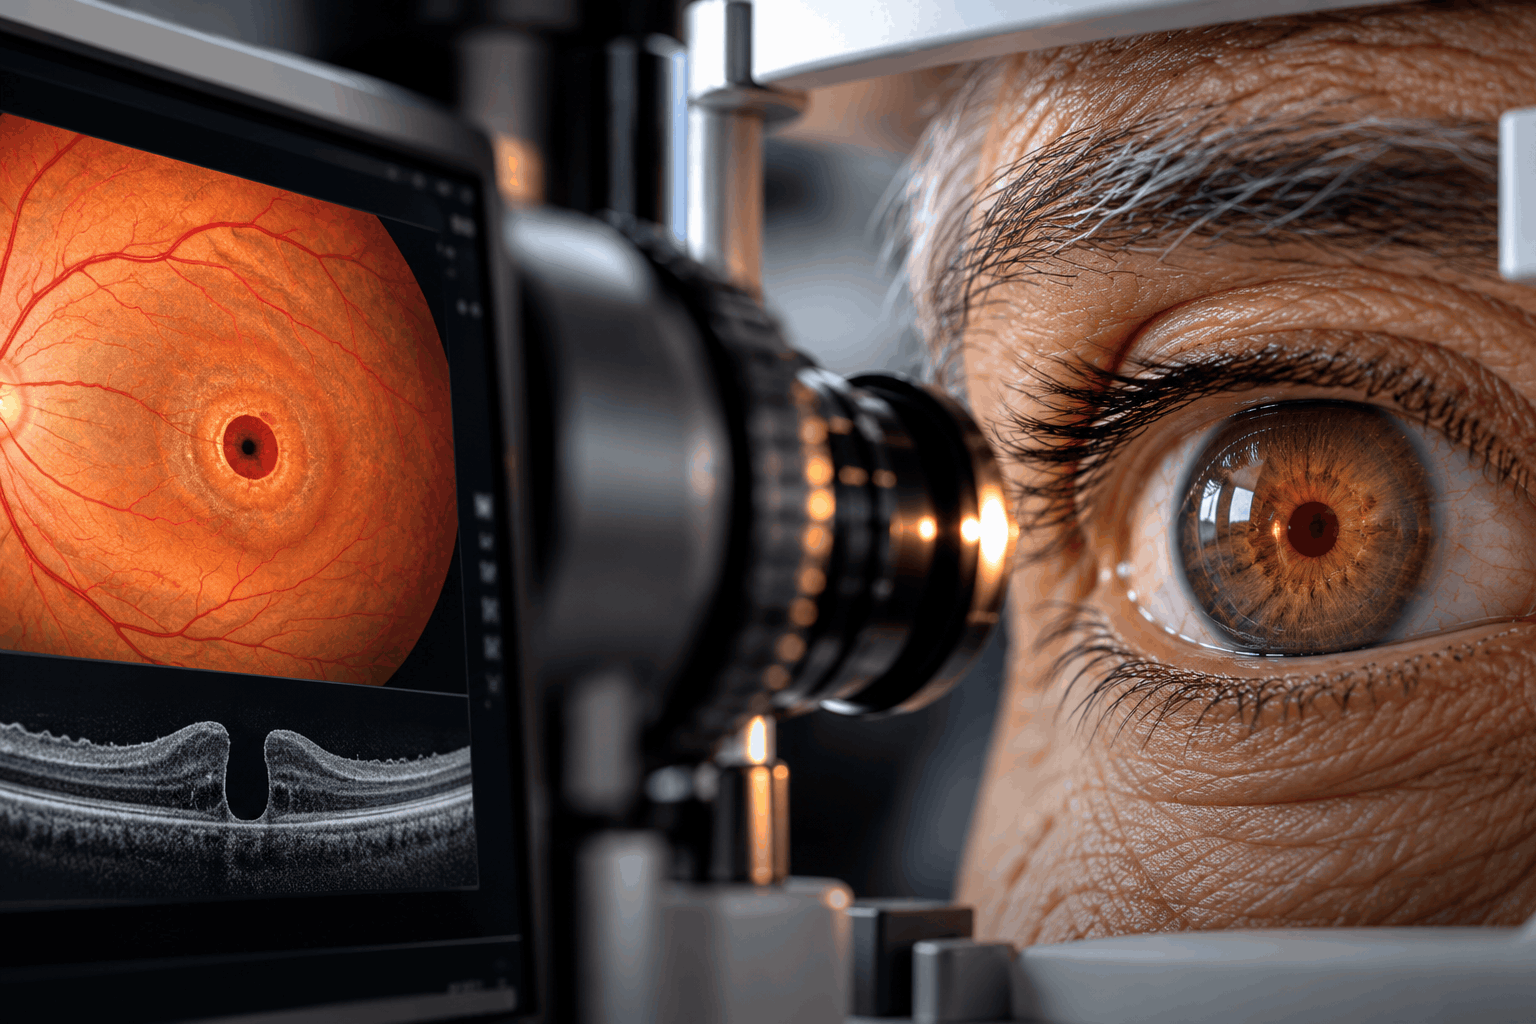
A macular hole is an opening that develops in the macula, the central part of the retina responsible for sharp, detailed vision.
The retina is the light-sensitive tissue at the back of the eye. The macula allows us to read, recognize faces, drive, and see fine details.
A full-thickness macular hole occurs when an opening extends through the full depth of the retinal tissue at the center of the macula.
Macular holes usually affect one eye, although the other eye may also be at risk.
The condition most commonly develops in adults over the age of 55 to 60 and is often related to changes in the vitreous gel inside the eye.
As the vitreous changes with age, it may pull on the macula. In some individuals, this traction causes the central retinal tissue to stretch and eventually develop a hole.
Macular holes may be classified according to their size, appearance, and relationship to vitreomacular traction. Optical coherence tomography (OCT) is used to assess these features.
A macular hole can cause blurred central vision, distortion of straight lines, or a small blind spot in the center of vision.
Peripheral vision is generally preserved, but difficulty with reading and other detailed visual activities can significantly affect daily life.
A macular hole is not the same as age-related macular degeneration (AMD). Although both conditions affect the macula, they have different causes and treatments.
Some small or early holes may close spontaneously, but most persistent full-thickness macular holes require surgery to achieve closure and improve the chances of visual recovery.
Early diagnosis and specialist assessment are important because the size and duration of the macular hole may influence treatment outcomes.
Symptoms
Symptoms of a macular hole usually affect central vision and may develop gradually over days, weeks, or months.
Common symptoms include:
• Blurred central vision.
• Straight lines appearing bent, wavy, or distorted.
• Difficulty reading small print.
• Missing letters or words while reading.
• A small dark, gray, or blurred spot in the center of vision.
• Difficulty recognizing faces.
• Problems seeing fine details.
• Reduced clarity when looking directly at an object.
• Difficulty performing activities that require precise central vision.
Macular holes are usually painless.
Symptoms commonly affect one eye, so they may go unnoticed when the other eye provides good vision.
The degree of visual impairment depends on the size, duration, and characteristics of the macular hole.
In some patients, distortion becomes more noticeable before significant blurring develops.
As the hole enlarges, central vision may become progressively worse.
IMPORTANT WARNING SIGNS
New or worsening distortion of straight lines, a central blind spot, or unexplained loss of central vision requires prompt ophthalmic assessment.
Sudden severe vision loss, a dark curtain across the visual field, or a sudden shower of new floaters requires urgent evaluation because another serious retinal condition may be present.
These symptoms should not be ignored, even if the eye is painless.
Causes
Most macular holes develop as a result of age-related changes in the vitreous gel and its relationship with the retina.
The vitreous is the transparent gel-like substance filling the inside of the eye.
As people age, the vitreous becomes more liquid and may gradually separate from the retinal surface. This process is called posterior vitreous detachment.
In some individuals, the vitreous remains firmly attached to the macula while separating from surrounding retinal tissue.
This creates traction, or pulling force, on the central retina.
Persistent vitreomacular traction can stretch the retinal tissue and lead to formation of a macular hole.
Other possible causes or associations include:
1. High Myopia
Eyes with significant nearsightedness may experience structural changes that increase the risk of certain types of macular holes.
2. Eye Trauma
A blunt injury to the eye can occasionally cause a traumatic macular hole, including in younger patients.
3. Epiretinal Membrane
A thin membrane on the retinal surface may contract and exert tangential traction on the macula, contributing to the formation of a hole in selected cases.
4. Other Retinal Conditions
Macular holes may occasionally occur in association with retinal detachment, chronic macular edema, or other retinal abnormalities.
In most patients, the condition develops spontaneously without an identifiable injury or systemic illness.
Macular holes are not contagious and are not usually caused by ordinary reading, screen use, or routine visual activities.
Identifying the underlying mechanism helps the retinal specialist determine the most appropriate treatment.
Risk Factors
Several factors are associated with an increased likelihood of developing a macular hole.
These include:
• Increasing age, particularly after age 55 to 60.
• Female sex.
• Age-related vitreous changes.
• Vitreomacular traction.
• A previous macular hole in the other eye.
• High myopia.
• Previous significant eye trauma.
• Certain retinal conditions involving traction or structural changes.
Most macular holes develop without a clearly identifiable preventable cause.
A macular hole in one eye increases the risk of developing a macular hole in the other eye, although most patients do not develop bilateral disease.
The ophthalmologist can evaluate the vitreoretinal interface in the unaffected eye and provide individualized monitoring recommendations.
Having a risk factor does not necessarily mean a macular hole will develop.
Patients with persistent new central visual distortion should undergo an eye examination even if they do not have any known risk factors.
Diagnosis
A macular hole is diagnosed through a detailed retinal examination, usually supported by optical coherence tomography (OCT).
The ophthalmologist evaluates the size and characteristics of the hole, the condition of the surrounding retinal tissue, and the presence of vitreomacular traction.
1. Medical History and Symptom Assessment
The doctor reviews the onset and duration of blurred or distorted central vision.
Questions may cover reading difficulties, previous eye injuries, high myopia, and retinal conditions.
2. Visual Acuity Testing
Visual acuity testing measures how clearly the patient sees.
It helps assess the impact of the macular hole on central vision and provides a baseline for monitoring treatment outcomes.
3. Dilated Fundus Examination
Eye drops are used to widen the pupil so the ophthalmologist can examine the macula and surrounding retina.
A macular hole may appear as a small, round defect in the central retina.
4. Optical Coherence Tomography (OCT)
OCT is the most important imaging investigation for diagnosing and evaluating macular holes.
It uses reflected light to produce detailed cross-sectional images of the retina.
OCT helps determine:
• Whether a full-thickness macular hole is present.
• The dimensions of the hole.
• Whether vitreomacular traction is present.
• The appearance of the surrounding retinal layers.
• Whether the hole is stable, enlarging, or closing.
• The structural response after treatment.
5. Amsler Grid Assessment
An Amsler grid may reveal distortion or missing areas of central vision.
It can be helpful for symptom monitoring, but it cannot replace OCT or a complete retinal examination.
6. Examination of the Other Eye
The ophthalmologist may assess the other eye for vitreomacular changes or abnormalities that could increase its risk of developing a macular hole.
7. Additional Retinal Imaging
Further imaging may be recommended if another retinal condition is suspected or the findings are atypical.
Not every patient requires all investigations.
The ophthalmologist uses clinical examination and OCT findings to decide whether observation or surgical treatment is most appropriate.
Treatment Options
Treatment of a macular hole depends on its size, duration, appearance on OCT, visual symptoms, and the presence of vitreomacular traction.
The main goal is to close the macular hole, preserve remaining central vision, and improve visual function when possible.
1. Observation and Monitoring
Some very small or early macular holes may close spontaneously.
In selected patients, the ophthalmologist may recommend careful observation with repeat OCT imaging.
However, spontaneous closure is not common for most established full-thickness macular holes.
Observation is not appropriate for every patient, particularly when the hole is enlarging or vision is deteriorating.
2. Pars Plana Vitrectomy
Vitrectomy is the principal surgical treatment for most persistent full-thickness macular holes.
During the procedure, the retinal surgeon removes the vitreous gel to relieve traction on the macula.
The surgeon commonly peels a thin membrane from the surface of the retina, called the internal limiting membrane (ILM), to improve the likelihood of hole closure.
A temporary gas bubble is usually placed inside the eye to support the macular hole while it heals.
The procedure may be performed under local or general anesthesia depending on the patient's clinical circumstances.
3. Gas Tamponade
The gas bubble acts as temporary internal support while the edges of the macular hole close.
It gradually becomes smaller and is naturally replaced by fluid produced inside the eye.
Vision is usually significantly blurred while the gas bubble remains present.
The duration of the bubble depends on the type of gas used and individual circumstances.
4. Postoperative Positioning
After surgery, some patients may be asked to maintain a particular head position, sometimes including face-down positioning.
Positioning requirements depend on the size and characteristics of the hole, surgical technique, and surgeon's assessment.
Face-down positioning may be especially important for larger holes, but it is not necessary for every patient.
Patients should follow the instructions provided by their retinal surgeon rather than using a standard positioning schedule.
5. Important Gas Bubble Precautions
If a gas bubble has been placed inside the eye:
• Do not travel by airplane while the bubble remains present.
• Avoid high-altitude travel until cleared by the surgeon.
• Do not receive nitrous oxide anesthesia or inhaled nitrous oxide pain relief while gas remains in the eye.
• Inform all medical and dental professionals that an intraocular gas bubble is present.
• Follow driving, activity, and positioning restrictions given by the surgeon.
Changes in atmospheric pressure or exposure to nitrous oxide can cause the gas bubble to expand dangerously, increasing eye pressure and risking permanent vision damage.
6. Recovery and Visual Improvement
The anatomical success of macular hole surgery is generally high, especially for suitable cases treated before longstanding damage develops.
However, successful closure does not guarantee a complete return to normal vision.
Visual improvement depends on factors including:
• The size of the macular hole.
• How long the hole has been present.
• The condition of the retinal photoreceptors.
• The presence of other retinal or ocular diseases.
• Whether the hole closes successfully.
Vision may improve gradually over several months after surgery.
7. Possible Surgical Complications
As with any intraocular procedure, vitrectomy carries potential risks.
These include:
• Cataract development or progression.
• Retinal tears or retinal detachment.
• Infection.
• Bleeding.
• Increased intraocular pressure.
• Persistent or recurrent macular hole.
• Incomplete visual recovery.
Some patients may require an additional operation if the hole does not close or reopens.
8. Follow-Up and Rehabilitation
Postoperative follow-up commonly includes visual acuity testing and OCT imaging to evaluate whether the hole has closed.
Prescribed eye drops, activity restrictions, and follow-up appointments are important for safe recovery.
Patients with persistent central visual impairment may benefit from magnifiers, improved lighting, and low vision support.
The decision to proceed with surgery should be made after detailed discussion of the likely benefits, risks, and expected visual outcomes with a vitreoretinal specialist.
Prevention & Care
There is no established way to reliably prevent most age-related macular holes.
However, awareness of central vision changes and timely retinal examinations may improve the opportunity for successful treatment.
Recommended measures include:
• Attend eye examinations according to your ophthalmologist's recommendations.
• Seek prompt assessment for new blurred or distorted central vision.
• Report straight lines appearing wavy or bent.
• Do not ignore a new central blind spot.
• Follow monitoring recommendations if you have previously had a macular hole in one eye.
• Use protective eyewear during activities that carry a risk of eye injury.
• Attend scheduled OCT follow-up appointments when observation has been recommended.
• Follow postoperative instructions carefully after retinal surgery.
Monitoring Central Vision
Patients may be advised to check each eye separately for distortion or missing areas of central vision.
An Amsler grid may help identify changes, although it does not replace professional retinal examination or OCT.
When Should You See an Eye Doctor?
Arrange prompt ophthalmic assessment if you notice:
• New distortion of straight lines.
• Blurred vision in the center of your visual field.
• Missing letters while reading.
• A new dark or blurred central spot.
• Gradual worsening of detailed vision.
Seek urgent medical attention for sudden severe vision loss, a dark curtain over the vision, or a sudden increase in flashes or floaters.
Care After Macular Hole Surgery
If you undergo vitrectomy:
• Use prescribed medications as directed.
• Attend all postoperative appointments.
• Follow any head-positioning instructions.
• Avoid flying and high-altitude travel while an intraocular gas bubble remains.
• Inform healthcare professionals about the gas bubble before anesthesia or procedures.
• Follow restrictions on driving, exercise, and heavy lifting.
• Contact the surgical team urgently for severe pain or worsening vision.
Early specialist assessment and adherence to the treatment plan can help protect central vision and improve the chances of a favorable outcome.
Frequently Asked Questions
What is a macular hole?
What causes a macular hole?
Is a macular hole the same as macular degeneration?
Can a macular hole cause blindness?
Is a macular hole painful?
Can a macular hole heal on its own?
How is a macular hole diagnosed?
What is the main treatment for a macular hole?
What happens during vitrectomy surgery?
Will I need to lie face down after surgery?
Why is a gas bubble used after surgery?
Can I fly after macular hole surgery?
Can I have general anesthesia while the gas bubble is present?
How long does recovery take?
Will vision return to normal after surgery?
Can a macular hole affect both eyes?
Can a macular hole return after surgery?
Are eye drops enough to treat a macular hole?
Does every macular hole require immediate surgery?
When should I seek an eye examination?
Our team can help you with an individual medical assessment.