
What Is It?
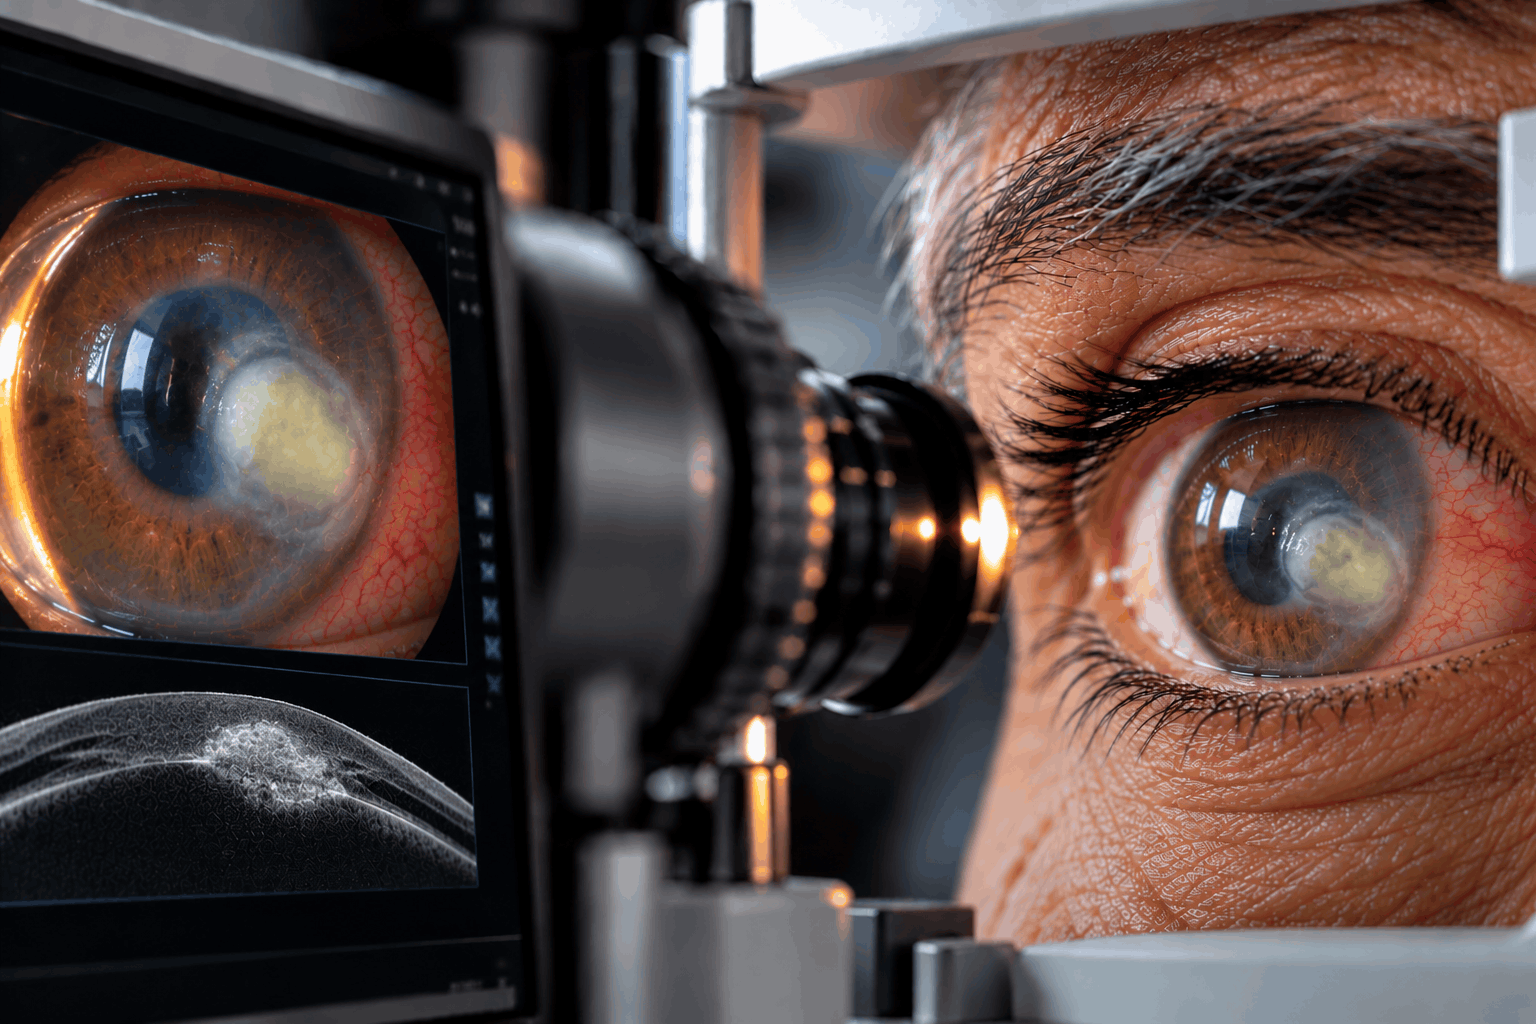
A corneal ulcer is an open wound or area of tissue loss on the cornea, the transparent, dome-shaped structure covering the iris and pupil at the front of the eye.
The cornea plays an essential role in focusing light onto the retina and maintaining clear vision. Its smooth, transparent surface also acts as an important protective barrier against infection and injury.
A corneal ulcer develops when the outer protective layer of the cornea, called the epithelium, becomes damaged or breaks down, often with inflammation or infection in the underlying corneal tissue.
Corneal ulcers are most commonly associated with infectious keratitis caused by bacteria, viruses, fungi, or microorganisms such as Acanthamoeba.
In some cases, noninfectious conditions, including severe dry eye, neurotrophic keratopathy, exposure-related damage, and inflammatory disorders, can also lead to corneal ulceration.
The condition may initially appear as a small white or gray area on the corneal surface, accompanied by redness, irritation, or pain.
As the ulcer progresses, infection and inflammation may spread deeper into the cornea, causing swelling, tissue damage, and reduced transparency.
Without prompt treatment, severe ulcers can lead to permanent corneal scarring, thinning, perforation, intraocular infection, and significant vision loss.
Corneal ulcers differ from simple corneal abrasions. An abrasion is generally a superficial scratch, whereas an ulcer involves an epithelial defect associated with underlying inflammation and may become progressively destructive.
A corneal ulcer is considered an ophthalmic emergency. Early diagnosis and treatment are essential to control the underlying cause, protect the corneal structure, and preserve vision.
Symptoms
Symptoms of corneal ulcers can range from moderate irritation to severe pain and significant visual disturbance. They may develop rapidly, particularly with certain bacterial infections.
Common symptoms include:
• Eye pain, which may be moderate or severe.
• Persistent redness, particularly around the cornea.
• Blurred or reduced vision.
• Increased sensitivity to light (photophobia).
• Excessive tearing or watery eyes.
• Yellow, white, or greenish eye discharge, particularly with bacterial infection.
• A foreign body sensation, as if sand or something sharp is inside the eye.
• Difficulty keeping the affected eye open.
• Eyelid swelling or irritation.
• A visible white or gray spot on the cornea.
• Increased discomfort when blinking.
• A cloudy appearance of the corneal surface.
Some patients experience intense pain even when the visible corneal changes are relatively subtle. This can occur with certain infections, including Acanthamoeba keratitis.
Symptoms may initially resemble conjunctivitis, but corneal ulcers are potentially much more serious.
Contact lens wearers should be particularly cautious when experiencing pain, redness, or blurred vision.
Seek emergency ophthalmic care for severe eye pain, a visible corneal white spot, worsening redness, light sensitivity, or any reduction in vision.
Do not wait for symptoms to improve on their own, as untreated corneal ulcers can progress quickly and threaten sight.
Causes
Corneal ulcers can develop from infectious or noninfectious causes. Identifying the underlying cause is essential because treatment differs significantly between conditions.
1. Bacterial Infections
Bacterial keratitis is a common cause of infectious corneal ulcers.
Bacteria can enter the cornea when its protective surface is damaged. Contact lens misuse, corneal injuries, and ocular surface disease increase susceptibility.
Organisms associated with bacterial corneal ulcers include Pseudomonas aeruginosa, Staphylococcus species, and Streptococcus species.
Some bacterial infections can progress rapidly and cause severe corneal damage.
2. Viral Infections
Herpes simplex virus can cause recurrent corneal infections and ulceration.
Herpes zoster, the virus associated with shingles, may also affect the cornea.
Viral keratitis can produce characteristic epithelial lesions and, in some cases, deeper corneal inflammation.
3. Fungal Infections
Fungal corneal ulcers may develop after trauma involving soil, plant material, or agricultural debris.
Common fungal organisms include Fusarium, Aspergillus, and Candida species.
Fungal infections may progress more slowly than some bacterial infections but can penetrate deeply into the cornea and be difficult to treat.
4. Parasitic Infections
Acanthamoeba keratitis is an uncommon but potentially severe infection caused by a free-living microorganism found in water and soil.
It is associated with contact lens exposure to contaminated water, including swimming, showering, or improper lens cleaning.
5. Corneal Trauma
Scratches, foreign bodies, chemical injuries, and other forms of corneal damage can disrupt the protective epithelial barrier and increase the risk of ulceration.
6. Severe Dry Eye and Ocular Surface Disease
Reduced tear production or poor tear-film quality may impair corneal protection and healing, particularly in severe cases.
7. Incomplete Eyelid Closure
Exposure keratopathy may develop when the eyelids cannot fully close, allowing the corneal surface to dry out and become damaged.
8. Reduced Corneal Sensation
Neurotrophic keratopathy occurs when corneal sensation is impaired, reducing the normal protective responses required for healing.
9. Inflammatory and Autoimmune Conditions
Certain immune-mediated disorders may cause peripheral corneal ulceration and thinning.
Because infectious and noninfectious ulcers can appear similar, an ophthalmologist must determine the most likely cause before selecting treatment.
Risk Factors
Several factors can increase the likelihood of developing a corneal ulcer.
Contact Lens Wear
Contact lens use is a major risk factor, particularly when lenses are worn overnight, used beyond their recommended replacement schedule, or handled without adequate hygiene.
Contact with Water While Wearing Lenses
Swimming, showering, or exposing contact lenses to tap water increases the risk of certain infections, including Acanthamoeba keratitis.
Poor Contact Lens Hygiene
Improper cleaning, inadequate disinfection, reusing old solution, or using contaminated lens cases can increase infection risk.
Corneal Injury
Scratches, foreign bodies, chemical exposure, and injuries involving plant or soil material can damage the corneal surface.
Previous Herpes Simplex Eye Infection
A history of ocular herpes increases the risk of recurrent corneal inflammation and ulceration.
Severe Dry Eye Disease
Insufficient tear protection may compromise the integrity of the corneal epithelium.
Eyelid Abnormalities
Incomplete eyelid closure, eyelid malposition, or other disorders that expose the cornea may increase the likelihood of surface breakdown.
Reduced Corneal Sensation
Damage to corneal nerves can impair protective blinking and normal wound healing.
Ocular Surface Disorders
Certain chronic inflammatory or cicatrizing eye diseases may compromise corneal health.
Use of Corticosteroid Eye Drops
Inappropriate or unsupervised steroid use can worsen some infections or mask their progression.
Immunosuppression
Certain medical conditions and immune-suppressing medications may increase susceptibility to infection or impair healing.
Previous Eye Surgery
Some postoperative conditions can temporarily compromise the corneal surface.
Having a risk factor does not mean that an ulcer will necessarily occur. Proper lens hygiene, protection from injury, and early treatment of ocular surface disorders can help reduce risk.
Diagnosis
A corneal ulcer requires prompt assessment by an ophthalmologist. Diagnosis involves examining the corneal surface, evaluating the depth and extent of tissue damage, and identifying the possible infectious or noninfectious cause.
1. Medical and Eye History
The ophthalmologist asks about:
• The onset and progression of pain, redness, and visual symptoms.
• Contact lens use and hygiene practices.
• Previous ocular infections or herpes simplex disease.
• Recent eye trauma or foreign body exposure.
• Exposure to swimming pools, tap water, or contaminated solutions.
• Previous eye surgery or use of steroid eye drops.
• Medical conditions that may affect immunity or corneal healing.
2. Visual Acuity Testing
Vision is measured to assess the effect of the ulcer on visual function and establish a baseline for monitoring recovery.
3. Slit-Lamp Examination
A slit-lamp microscope allows detailed inspection of the cornea and surrounding eye structures.
The ophthalmologist evaluates the ulcer's location, size, depth, surrounding inflammation, and any associated corneal thinning.
4. Fluorescein Staining
A special dye called fluorescein highlights areas where the corneal epithelium is missing or damaged.
This helps define the extent and shape of the ulcer.
5. Corneal Scraping and Microbiological Testing
In selected cases, particularly larger, central, deep, unusual, or treatment-resistant ulcers, the ophthalmologist may collect a corneal sample.
Laboratory microscopy, culture, and other tests can help identify bacteria, fungi, or other microorganisms responsible for infection.
6. Polymerase Chain Reaction (PCR) Testing
PCR may be used in selected cases to detect specific pathogens, such as herpes viruses or Acanthamoeba.
7. Corneal Imaging
Anterior segment optical coherence tomography (OCT) may help assess corneal thickness, ulcer depth, or structural changes.
In vivo confocal microscopy may be useful in specialized centers when investigating certain fungal or Acanthamoeba infections.
8. Evaluation of the Anterior Chamber
The ophthalmologist examines the interior of the front part of the eye for inflammation, including a hypopyon, which is an accumulation of inflammatory cells.
9. Follow-Up Assessment
Repeated examinations are often necessary to monitor the response to treatment, healing of the epithelial defect, and any signs of progression.
Some severe cases require very frequent follow-up or hospital-based management.
The diagnostic approach depends on the clinical findings, and treatment should not be unnecessarily delayed when a serious infection is suspected.
Treatment Options
Treatment of a corneal ulcer must begin promptly and is determined by the suspected cause, ulcer severity, location, and response to therapy.
A corneal ulcer is an ophthalmic emergency, and patients should not attempt to treat it using leftover eye drops or home remedies.
1. Antibiotic Eye Drops
Bacterial corneal ulcers are treated with appropriate topical antibiotics.
Depending on the severity of infection, the ophthalmologist may prescribe broad-spectrum antibiotic drops or fortified preparations.
Severe cases may require very frequent administration during the initial treatment period.
Therapy may be adjusted according to clinical response or laboratory results.
2. Antiviral Treatment
Corneal ulcers caused by herpes simplex or other selected viral infections may require antiviral eye drops, ointments, or oral antiviral medication.
The exact treatment depends on the type of viral keratitis and the affected corneal layers.
3. Antifungal Therapy
Fungal corneal infections require specialized antifungal medication.
Treatment may involve prolonged topical antifungal therapy and, in selected severe cases, systemic or other additional approaches.
Fungal ulcers may require extended follow-up because healing can be slow.
4. Anti-Acanthamoeba Treatment
Acanthamoeba keratitis usually requires intensive, prolonged treatment with specific anti-amoebic medications.
Management should be supervised by an ophthalmologist experienced in corneal infection.
5. Cycloplegic Eye Drops
Certain dilating eye drops may be prescribed to reduce discomfort associated with internal eye inflammation and ciliary muscle spasm.
6. Pain Management
The ophthalmologist may recommend appropriate oral pain medication and other supportive measures.
Topical anesthetic eye drops should not be used repeatedly at home unless specifically directed under a supervised medical protocol, because misuse can damage the cornea and interfere with healing.
7. Management of Underlying Ocular Surface Disease
When ulceration is related to severe dry eye, exposure, reduced corneal sensation, or inflammatory disorders, treatment must also address the underlying problem.
Approaches may include preservative-free lubrication, protective ocular surface measures, or other specialist treatments.
8. Corticosteroid Eye Drops
Steroid eye drops are not routine initial treatment for an undiagnosed corneal ulcer.
In selected circumstances, an ophthalmologist may consider them after appropriate antimicrobial therapy and assessment.
Steroids can worsen certain infections, particularly fungal, Acanthamoeba, and some viral infections, and must never be started without specialist guidance.
9. Surgical or Procedural Management
Severe ulcers associated with progressive thinning, threatened perforation, or failure of medical therapy may require additional procedures.
Depending on the situation, these may include tissue adhesive, amniotic membrane transplantation, temporary protective measures, or corneal transplantation.
Therapeutic corneal transplantation may be necessary when infection cannot be adequately controlled or the structural integrity of the eye is threatened.
In other patients, optical corneal transplantation may be considered after the infection has resolved if significant scarring continues to impair vision.
10. Follow-Up and Recovery
Frequent ophthalmic follow-up is essential, particularly in severe or central ulcers.
The ophthalmologist monitors the ulcer's size, depth, infection control, epithelial healing, and effect on vision.
Patients must follow the prescribed treatment schedule carefully and should not stop medication without medical advice.
Contact lenses should not be worn during active disease and should only be resumed after the ophthalmologist confirms that it is safe.
Early appropriate treatment can significantly improve outcomes, but severe ulcers may leave permanent scarring or visual impairment.
Prevention & Care
Many corneal ulcers can be prevented through proper eye hygiene, safe contact lens use, protection from injury, and early treatment of ocular surface conditions.
Recommended preventive measures include:
• Wash and dry your hands before touching contact lenses.
• Clean and disinfect reusable lenses exactly as recommended by your eye care professional.
• Never use tap water, saliva, or homemade solutions to clean or store contact lenses.
• Avoid swimming, showering, or using hot tubs while wearing contact lenses.
• Do not sleep in contact lenses unless specifically prescribed for overnight use; even then, infection risk is higher.
• Replace contact lenses according to the recommended schedule.
• Replace contact lens cases regularly and avoid topping up old disinfecting solution.
• Stop wearing contact lenses immediately if eye pain, redness, or unusual discomfort occurs.
• Wear appropriate protective eyewear during activities that may cause eye injuries.
• Seek prompt assessment after a corneal scratch, chemical exposure, or foreign body injury.
• Follow recommended treatment for dry eye, eyelid disorders, and other ocular surface conditions.
• Avoid using steroid or anesthetic eye drops without ophthalmic supervision.
• Attend regular eye examinations when managing chronic ocular diseases.
If a corneal ulcer is suspected:
• Remove contact lenses immediately.
• Do not rub the affected eye.
• Do not apply an eye patch unless an ophthalmologist specifically recommends it.
• Avoid using leftover antibiotic, steroid, or anesthetic drops.
• Arrange urgent, same-day ophthalmic assessment.
Patients undergoing treatment should follow medication instructions carefully and attend all scheduled appointments.
Increasing pain, worsening redness, enlarging corneal opacity, or declining vision during treatment requires immediate reassessment.
Prevention, rapid recognition, and timely specialist care are essential to protecting the cornea and reducing the risk of permanent vision loss.
Frequently Asked Questions
What is a corneal ulcer?
Is a corneal ulcer a medical emergency?
What are the most common symptoms of a corneal ulcer?
What causes corneal ulcers?
Can wearing contact lenses cause a corneal ulcer?
Can a corneal ulcer cause permanent vision loss?
Is a corneal ulcer contagious?
How is a corneal ulcer diagnosed?
Can a corneal ulcer heal on its own?
How are bacterial corneal ulcers treated?
Can eye drops treat a fungal corneal ulcer?
What is Acanthamoeba keratitis?
Are steroid eye drops safe for corneal ulcers?
How long does a corneal ulcer take to heal?
Will I need a corneal transplant?
Can I wear contact lenses while being treated?
How can I prevent corneal ulcers?
When should I seek emergency eye care?
Our team can help you with an individual medical assessment.