
What Is It?
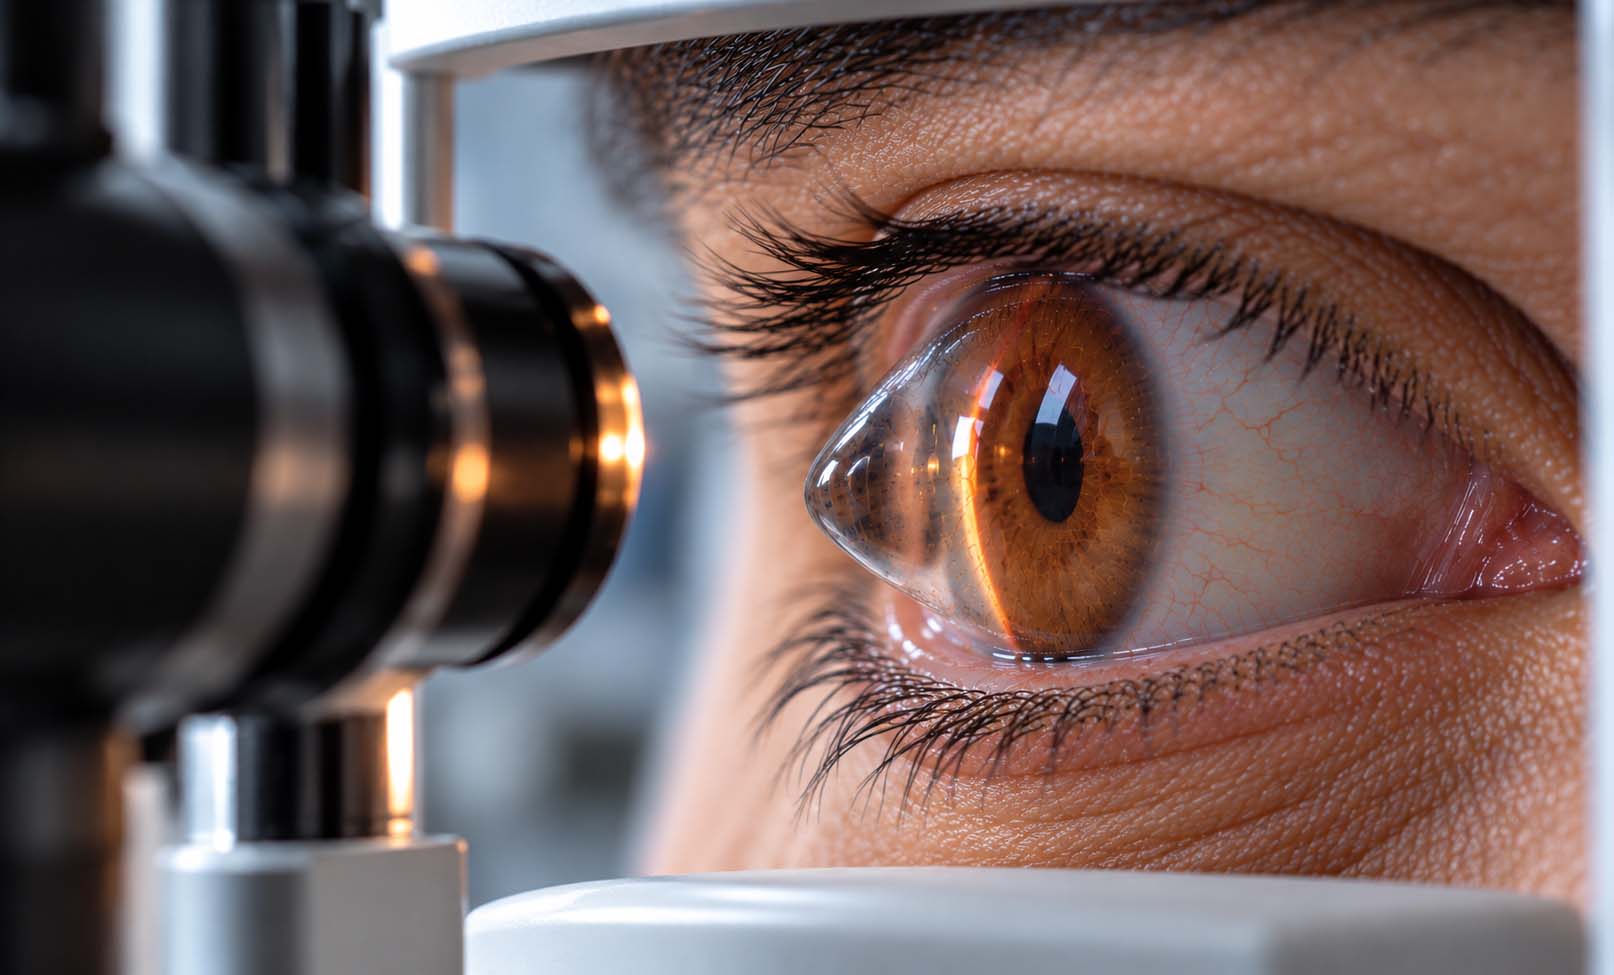
Keratoconus is a condition that causes the cornea, the transparent front surface of the eye, to become progressively thinner and bulge into an irregular, cone-like shape.
A healthy cornea has a smooth, curved surface that helps focus light onto the retina. In keratoconus, changes in the corneal shape prevent light from focusing properly, leading to irregular astigmatism, blurred vision, and visual distortion.
Keratoconus commonly begins during adolescence or early adulthood, although it can develop at other ages. It usually affects both eyes, but one eye may be more severely affected than the other.
The condition may progress over several years, particularly in younger patients. However, the rate and severity of progression vary considerably.
In mild cases, vision may be corrected with eyeglasses or contact lenses. As the cornea becomes more irregular, specialized contact lenses may be needed to improve visual clarity.
For patients with progressive keratoconus, corneal collagen cross-linking can help strengthen the cornea and reduce further deterioration.
Advanced cases may require additional procedures or corneal transplantation when adequate vision cannot be achieved with other treatments.
Early detection, accurate corneal imaging, and regular follow-up are essential for preserving vision and identifying patients who may benefit from treatment.
Symptoms
Keratoconus symptoms vary according to the severity and progression of corneal changes.
Common symptoms include:
• Blurred or distorted vision.
• Increasing nearsightedness or irregular astigmatism.
• Frequent changes in eyeglass prescriptions.
• Difficulty achieving clear vision with ordinary glasses.
• Increased sensitivity to bright lights and glare.
• Halos or streaks around lights, especially at night.
• Double or multiple images in one eye (monocular ghosting).
• Difficulty driving at night.
• Reduced contrast and clarity of fine details.
Symptoms may develop gradually and become more noticeable as the cornea changes shape.
The two eyes may be affected differently, resulting in unequal visual quality.
In advanced keratoconus, corneal scarring can cause more persistent visual impairment.
Rarely, sudden corneal swelling called acute corneal hydrops can develop, causing rapid vision deterioration, clouding of the cornea, discomfort, or pain.
Sudden painful loss of vision or new corneal clouding requires urgent ophthalmic assessment.
Because early keratoconus can resemble ordinary astigmatism, specialized corneal imaging may be needed when vision changes continue despite updated glasses.
Causes
The exact cause of keratoconus is not fully understood.
It is considered a multifactorial condition involving genetic susceptibility, structural changes within the cornea, and environmental or mechanical influences.
The cornea contains collagen fibers that help maintain its strength and shape. In keratoconus, changes in corneal tissue and its biomechanical properties contribute to progressive thinning and irregular bulging.
Several mechanisms may be involved:
1. Genetic Susceptibility
Keratoconus can occur in families, although many patients have no known family history.
Multiple genetic factors may contribute to an individual's susceptibility.
2. Corneal Structural Changes
Alterations in collagen organization and corneal tissue strength may reduce the cornea's ability to maintain its normal shape.
3. Eye Rubbing
Frequent or vigorous eye rubbing is strongly associated with keratoconus and may contribute to its development or progression.
4. Allergic Eye Conditions
Eye allergies can produce itching and encourage repeated eye rubbing, potentially worsening mechanical stress on the cornea.
Keratoconus is not caused by a bacterial or viral infection, and it is not contagious.
In many individuals, no single identifiable cause explains why the condition develops.
Risk Factors
Several factors are associated with an increased likelihood of developing keratoconus or experiencing progression.
These include:
• A family history of keratoconus.
• Younger age, especially adolescence and early adulthood.
• Frequent or vigorous eye rubbing.
• Allergic eye disease and persistent eye itching.
• Atopic conditions, including eczema, asthma, or allergic rhinitis.
• Certain genetic or connective tissue disorders.
• Down syndrome.
• A previously diagnosed keratoconus condition in the other eye.
Young patients may experience faster progression and often require closer monitoring.
A family history does not mean keratoconus will necessarily develop, but relatives may benefit from professional eye assessment when clinically indicated.
Patients with persistent eye allergies should seek appropriate treatment to reduce itching and the urge to rub their eyes.
Diagnosis
Keratoconus is diagnosed through a comprehensive ophthalmic examination combined with specialized assessment of corneal shape and thickness.
The ophthalmologist may perform the following tests:
1. Visual Acuity and Refraction
Visual acuity testing measures how clearly the patient sees.
Refraction identifies nearsightedness and astigmatism and helps determine whether ordinary glasses provide adequate vision correction.
2. Slit-Lamp Examination
A specialized microscope allows the ophthalmologist to examine the cornea for thinning, irregular shape, scarring, and other clinical signs of keratoconus.
3. Corneal Topography
Corneal topography maps the curvature of the corneal surface.
It helps identify characteristic steepening and irregular astigmatism associated with keratoconus.
4. Corneal Tomography
Corneal tomography provides detailed information about the anterior and posterior corneal surfaces, elevation, and thickness distribution.
It is particularly valuable for detecting early keratoconus and assessing progression.
5. Pachymetry
Pachymetry measures corneal thickness.
Progressive thinning may support the diagnosis and help determine suitability for certain treatments.
6. Corneal Imaging and Progression Monitoring
Serial corneal scans allow the ophthalmologist to compare changes in corneal curvature, thickness, and other parameters over time.
This helps determine whether the disease is stable or progressing.
Not every patient requires every investigation. The ophthalmologist selects the appropriate tests and recommends follow-up based on age, corneal findings, and progression risk.
Patients wearing contact lenses may be asked to stop wearing them temporarily before corneal measurements to improve test accuracy.
Treatment Options
Keratoconus treatment has two main goals: improving visual clarity and preventing or slowing further changes in corneal shape.
The treatment plan depends on the severity of corneal irregularity, age, progression, corneal thickness, and the patient's visual needs.
1. Eyeglasses and Soft Contact Lenses
In early keratoconus, eyeglasses or selected soft contact lenses may provide satisfactory vision correction.
However, ordinary glasses become less effective as irregular astigmatism increases.
These options improve vision but do not prevent keratoconus progression.
2. Specialized Contact Lenses
Rigid gas-permeable (RGP) lenses and scleral lenses can provide improved vision by creating a more regular optical surface.
Depending on the patient's needs, other options may include hybrid or customized specialty contact lenses.
Scleral lenses rest on the white part of the eye and vault over the cornea, which can improve comfort and visual quality in selected patients.
Specialized fitting and regular follow-up are necessary.
Contact lenses improve optical correction but do not reliably stop progressive corneal thinning.
3. Corneal Collagen Cross-Linking (CXL)
Corneal cross-linking is an established treatment for progressive keratoconus.
The procedure uses riboflavin (vitamin B2) eye drops and controlled ultraviolet-A (UVA) light to increase the biomechanical strength of corneal tissue.
Its main purpose is to slow or stop further corneal shape deterioration, reducing the risk of progressive visual impairment.
Cross-linking is particularly important in younger patients and those showing evidence of progression.
The procedure does not guarantee improved vision or eliminate the need for glasses or contact lenses.
Some patients may continue to progress after treatment, so follow-up remains essential.
The ophthalmologist evaluates corneal thickness, disease progression, and other factors to determine whether the procedure is suitable.
Possible risks include pain during early healing, infection, corneal haze, delayed epithelial healing, or scarring.
4. Intracorneal Ring Segments
In selected patients, small ring segments may be implanted within the cornea to modify its shape and reduce irregularity.
This may improve visual function or make contact lens fitting easier.
Ring segments are not suitable for every patient and do not replace cross-linking when disease progression needs to be controlled.
5. Corneal Transplantation
In advanced keratoconus, transplantation may be considered when severe thinning, scarring, or irregularity prevents satisfactory vision with other treatments.
Depending on the condition of the cornea, surgical options may include:
• Deep Anterior Lamellar Keratoplasty (DALK), which replaces affected corneal layers while preserving the patient's healthy inner endothelial layer.
• Penetrating Keratoplasty (PK), which replaces the full thickness of the cornea with donor tissue.
Corneal transplantation can improve visual function in appropriately selected patients, but recovery may be prolonged.
Some patients continue to require glasses or contact lenses after transplantation.
6. Long-Term Monitoring
Regular follow-up helps identify disease progression and evaluate the effectiveness of treatment.
Repeat refraction, visual acuity testing, and corneal topography or tomography may be recommended.
The ophthalmologist determines follow-up intervals according to the patient's age, disease severity, and progression risk.
Early treatment of progressive keratoconus can reduce the likelihood of advanced corneal complications and the need for transplantation.
Prevention & Care
There is no guaranteed way to prevent keratoconus because its causes are complex and partly genetic.
However, early diagnosis, regular monitoring, and avoidance of harmful eye-rubbing habits may help reduce progression risk and protect visual function.
Recommended measures include:
• Avoid vigorous or repeated eye rubbing.
• Seek treatment for eye allergies and persistent itching.
• Attend regular ophthalmic examinations when keratoconus is suspected or diagnosed.
• Follow recommended corneal topography or tomography monitoring schedules.
• Discuss cross-linking promptly if progression is identified.
• Use prescribed glasses or contact lenses correctly.
• Maintain proper contact lens hygiene and follow professional fitting instructions.
• Avoid sleeping in contact lenses unless specifically advised by the treating eye care professional.
• Follow postoperative instructions after cross-linking or corneal surgery.
• Inform the ophthalmologist about any family history of keratoconus.
When Should You See an Eye Doctor?
Arrange an eye examination if you experience:
• Increasing or frequently changing astigmatism.
• Blurred vision that is not adequately corrected with glasses.
• Increasing glare or difficulty with night vision.
• Noticeably different vision between the two eyes.
• Persistent eye rubbing or itching, particularly with worsening vision.
Seek urgent ophthalmic assessment if you develop sudden corneal clouding, significant eye pain, or a rapid reduction in vision.
Children and young adults with suspected keratoconus may need particularly close follow-up because progression can occur more rapidly.
Early diagnosis and appropriate management provide the best opportunity to preserve useful vision.
Frequently Asked Questions
What is keratoconus?
Is keratoconus the same as astigmatism?
At what age does keratoconus usually begin?
Can keratoconus affect both eyes?
What causes keratoconus?
Is keratoconus hereditary?
Can keratoconus cause blindness?
Can keratoconus be cured?
What is corneal cross-linking?
Does cross-linking improve vision immediately?
Will I need contact lenses after cross-linking?
Can keratoconus be treated without surgery?
When is corneal transplantation needed?
Can rubbing my eyes make keratoconus worse?
Is LASIK suitable for people with keratoconus?
How is keratoconus diagnosed?
Does keratoconus always get worse?
How often should keratoconus be monitored?
Our team can help you with an individual medical assessment.